Libido is easy to dismiss as “just stress” or “just hormones”.
But when your sex drive changes and stays changed, it can be a clue that something else in your health has shifted too.
Desire is influenced by sleep, medication, mental load, circulation, hormone availability and what is happening in your life at the time. Sometimes the reason is temporary. Sometimes the change is worth looking at more closely.
That is why libido deserves more than a quick assumption.
So, we’ll walk you through what libido actually means, why desire and physical response can change separately, what can sit behind a sustained drop in sex drive, and where biomarkers can add useful context.
Along the way, let’s talk about how sleep, medication, mental load, circulation and hormone availability can shape libido, and when a change is more likely to be temporary versus worth investigating further.
Libido is your level of sexual desire, but it is more useful to think of it as how available you feel for sex than as a fixed trait you either have or do not have.
There is no universal “normal”. Some people naturally think about sex often. Others do not. Libido can also move across different stages of life, during periods of poor sleep, after medication changes, or when your health changes. The useful comparison is not with someone else. It is with your own baseline.
Desire and physical response are different. You can feel mentally interested in sex but find that your body is slower to respond. Or the body can respond physically even when the desire is not really there.
That difference matters because a drop in desire may point you towards a different set of questions than a new problem with erection, lubrication, sensitivity or arousal.
Sexual desire does not always begin with a sudden feeling of “wanting sex”.
Research has challenged the idea that desire must always come first. Rosemary Basson’s work on sexual response showed that, particularly in long-term relationships, desire can develop after sexual or emotional engagement has already begun rather than appearing spontaneously beforehand.
That gives us two useful patterns:
Responsive desire is not a weaker version of libido. It is a recognised pattern of sexual response, and research suggests it is especially relevant for understanding desire in established relationships.
That distinction matters because someone can think their libido has “disappeared” when what has actually changed is the context that usually allows desire to emerge.
Stress can take up mental space. Poor recovery can make it harder to feel physically available. Relationship dynamics can also change the conditions in which desire normally appears.
So low spontaneous desire on its own does not automatically mean low libido.
A better question is:
Has the way desire normally shows up for you changed?
And one important caveat: spontaneous and responsive desire are useful models, not rigid biological categories. Sexual desire is shaped by biological, cognitive and emotional factors and does not always fit neatly into one pattern.

Sexual desire is heavily filtered through the brain.
Before you consciously feel interested in sex, your brain is already processing fatigue, attention, mood, stress, past experience, and the context you are in. That is why libido can feel very different on two days even when nothing obvious has changed hormonally.
Chemical signalling matters too, but not in a simple “high or low” way.
The important point is this:
A lower sex drive can happen even when hormone levels look completely normal, because desire is also being shaped by what the brain is doing with stress, attention, mood, and reward.
Your body can be interested in sex and still not feel ready for it.
That is where the autonomic nervous system comes in. It helps regulate the shift between being on alert and being relaxed enough for physical arousal to happen properly.
When stress stays high for too long, the body keeps prioritising what feels urgent. You might still want intimacy, but the physical response can become less reliable because your system is still acting like it has something else to deal with first.
This is why poor sleep, constant pressure, or feeling permanently “switched on” can affect more than mood. They can also change how easily the body moves into arousal.
So the issue is not that one side is “good” and the other is “bad”.
It is whether your body can actually shift gears when it needs to.
Sometimes desire is still there, but the body is not responding in the same way.
That is where blood flow comes in.
Sexual arousal depends on blood vessels widening and increasing blood flow to genital tissue. If that vascular response becomes less efficient, physical sexual response can change even when libido itself has not.
This is why sexual response can sometimes overlap with cardiovascular and metabolic health. Blood pressure, glucose regulation, lipid burden and endothelial function can all affect how well those blood vessels respond.
The key distinction is:
Libido is about desire. Blood flow is about how well the body responds to it.
Hormones influence libido in everyone, but they do not follow the same pattern in men and women.
The biggest difference is timing.
In men, hormone levels tend to follow a stronger daily rhythm. In women, they can shift across the menstrual cycle and then change again across different life stages.
This means that the same hormone result can have a very different meaning depending on when it was measured and what else is happening in the body.
Testosterone follows a circadian rhythm and is usually higher earlier in the day before gradually declining.
Sleep matters here too. Testosterone production is closely linked to sleep, so disrupted sleep can affect hormone levels as well as energy and sexual function.
That is why the timing of testosterone testing matters. A morning result and an afternoon result are not directly interchangeable.
A few hormones are especially relevant:
So when libido changes, it makes more sense to look at testosterone alongside SHBG, prolactin, thyroid function, sleep quality and the wider metabolic picture rather than relying on one number.
Could your testosterone levels be affecting your sex drive? Explore testosterone testing with Axo Longevity
In women: the hormonal picture is more complex
In women, there is often no single hormonal baseline to compare against.
Oestradiol and progesterone rise and fall across the menstrual cycle, while testosterone and SHBG can shift too. That means desire, lubrication, sensitivity and comfort can feel different at different points in the month without anything necessarily being wrong.
A few hormones are especially important here:
Around ovulation, rising oestradiol can coincide with greater sexual interest or physical responsiveness for some women. After ovulation, progesterone becomes more prominent and the experience can change again.
But the monthly cycle is only one layer.
Pregnancy and breastfeeding can shift hormone levels substantially. Perimenopause can make cycles less predictable before menopause lowers oestrogen more consistently. Hormonal contraception can change the picture again.
That also makes testing harder to interpret.
A result is not just about what the number is. You also need to know when in the cycle it was measured, whether cycles are regular, what life stage the person is in, and whether hormonal medication is involved.
And even with all of that context, hormone levels do not map neatly onto libido.
A single oestradiol or testosterone result rarely explains a change in desire on its own. It becomes more useful when it is read alongside symptoms, cycle timing, physical response and the wider health picture.
Noticing changes in your libido during perimenopause or menopause? Explore menopause testing with Axo Longevity
In women, context is part of the result.
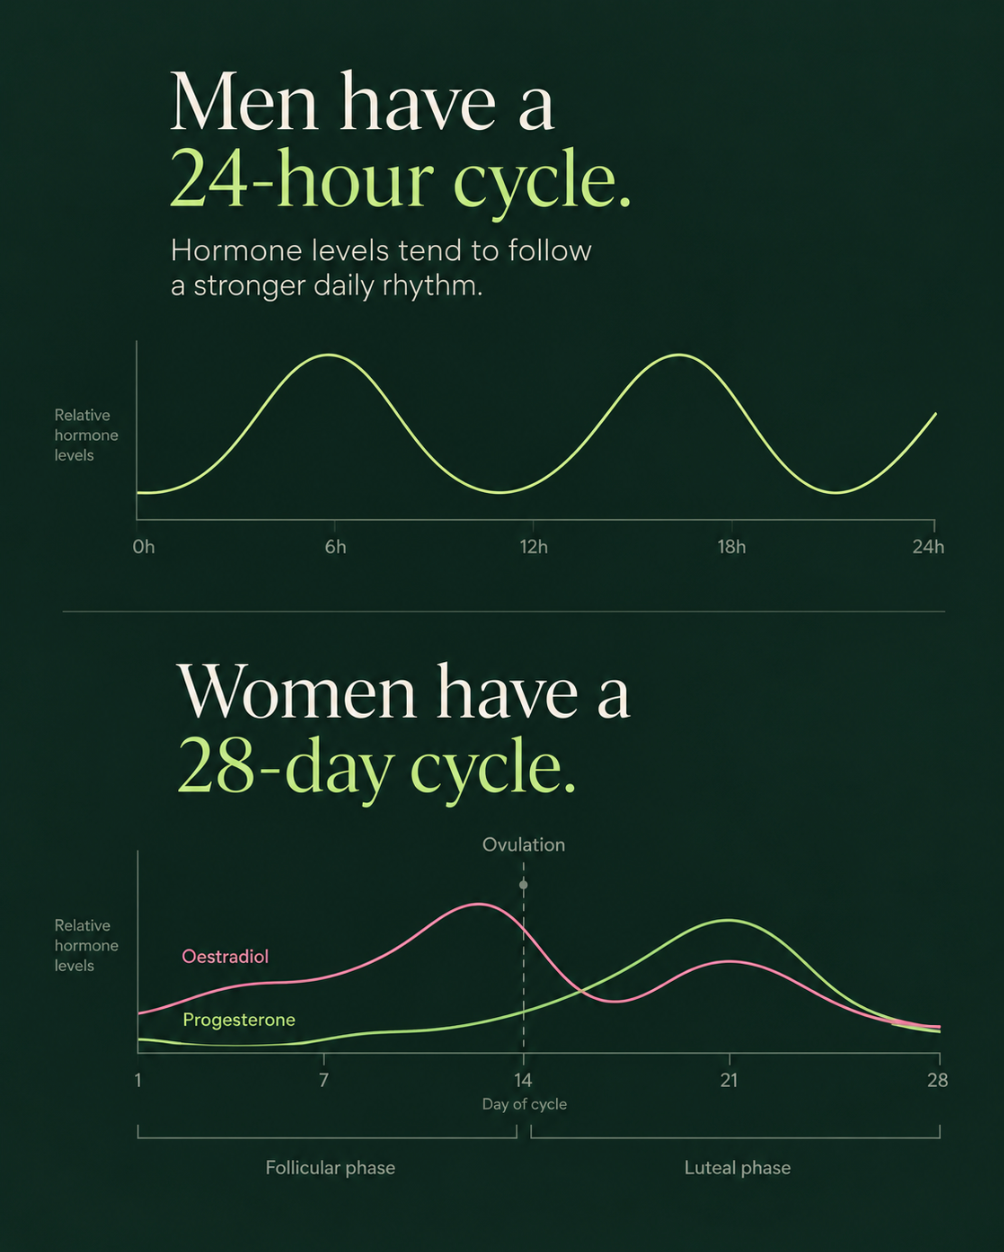
The systems behind libido overlap, but the way they fluctuate is not identical.
Libido does not stay biologically static.
In women, pregnancy, breastfeeding, starting or stopping hormonal contraception, perimenopause and menopause can all change the hormonal environment quite dramatically. These shifts can affect desire directly, but they can also change lubrication, tissue comfort, sleep and energy, which then influence sexual experience in their own way.
In men, the picture often changes more gradually. Ageing, sleep quality, body composition, metabolic health and vascular function can all affect testosterone availability and physical sexual response over time.
That does not mean libido should inevitably decline with age.
It means the biological context around it changes, and those changes can sometimes explain why sex drive feels different from one stage of life to another.
There is no blood test that can tell you why your sex drive has changed.
What testing can do is help answer more specific questions.
The useful part is not finding one “libido biomarker”.
It is understanding which biological system is most likely to be contributing and whether the data supports that idea.
A change in libido can come from more than one place, which is why looking at one hormone in isolation rarely gives you the full answer.
With Axo Longevity, you can test 100+ lab markers across 36+ areas of health and see how your hormone, metabolic and cardiovascular data fits together.
You’ll also get your Axo Longevity Health Score, biological age, and a personalised action plan based on your results.
If your sex drive has changed and you want to understand what may be happening underneath, this is a good place to start.
[Book your Axo Longevity blood test]
This article is for educational purposes only and is not a substitute for medical advice, diagnosis or treatment. Changes in libido or sexual function can have biological, psychological, medication-related or relationship-related causes that cannot be assessed through biomarkers alone.
If a change is persistent, causing distress or accompanied by other symptoms, speak with a qualified healthcare professional. Do not stop or change prescribed medication without medical guidance.